Our New FDA-Approved Treatment: Learn More

Updated Efficacy and Safety of Taletrectinib in Patients With Advanced ROS1+ NSCLC After Prior Entrectinib Exposure: Results From the Global TRUST-II Study

Maurice Pérol,1 Sara Cresta,2 Yuki Shinno,3 Pascale Tomasini,4 Lyudmila Bazhenova,5 Ernest Nadal,6 Wei Wang,7 Xianyu Zhang,7 Huan Huang,7 Santiago Viteri,8 Geoffrey Liu9

1Léon Bérard Cancer Center, Lyon, France; 2Fondazione IRCCS Istituto Nazionale dei Tumori, Milan, Italy; 3National Cancer Center Hospital, Tokyo, Japan; 4Hôpitaux Nord, CHU de Marseille, Marseille, France; 5UC San Diego Moores Cancer Center, San Diego, CA, USA; 6Catalan Institute of Oncology (ICO) IDIBELL, L’Hospitalet, Barcelona, Spain; 7Nuvation Bio Inc., New York, NY, USA; 8UOMI Cancer Center, Clinica Mi Tres Torres, Barcelona, Spain; 9Princess Margaret Cancer Centre, Temerty School of Medicine, University of Toronto, Toronto, ON, Canada

Presented at the European Society of Medical Oncology Congress | October 23–27, 2026 | Madrid, Spain
For more information, please contact Dr Maurice Pérol: maurice.perol@lyon.unicancer.fr

Jump to a section:

Background

  • Taletrectinib is a next-generation, CNS-active, selective ROS1 TKI approved in the United States, Japan, and China for patients with locally advanced or metastatic ROS1+ NSCLC1–5
  • In the global Phase 2 TRUST-II (NCT04919811) study, taletrectinib demonstrated robust overall and IC efficacy, and a manageable safety profile, in both TKI-naïve and TKI-pretreated patients with ROS1+ NSCLC6,7
  • Here we report updated efficacy and safety data from the TRUST-II study in patients previously treated with entrectinib, another CNS-active TKI

Methods

  • TRUST-II (NCT04919811) is a global, multicenter, pivotal, Phase 2 study of taletrectinib in patients with ROS1+ NSCLC, including both TKI-naïve and TKI-pretreated patients

TRUST-II Study Design
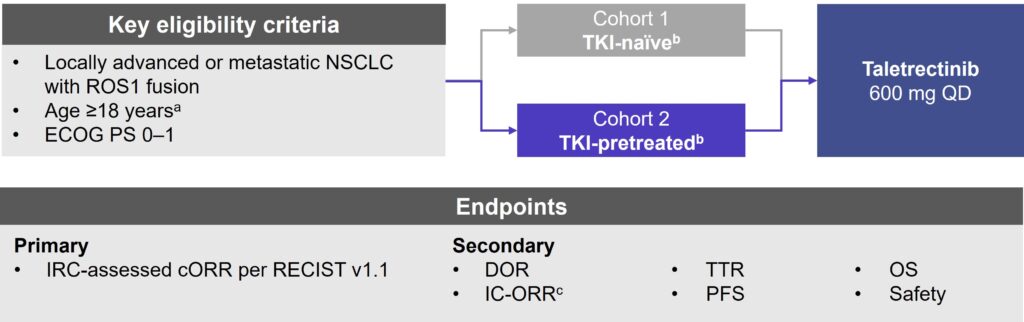
aOr ≥20 years, as required by local regulations. bRegistrational cohorts are shown. cAssessed by IRC per mRECIST v1.1.

  • Patients in Cohort 2 received prior treatment with crizotinib or entrectinib; patients may also have received prior chemotherapy with or without immunotherapy
  • Here, we report updated efficacy and safety in the 10 patients from Cohort 2 with ≥1 measurable baseline lesion per RECIST v1.1 by IRC, who experienced disease progression on entrectinib and subsequently received taletrectinib 600 mg QD
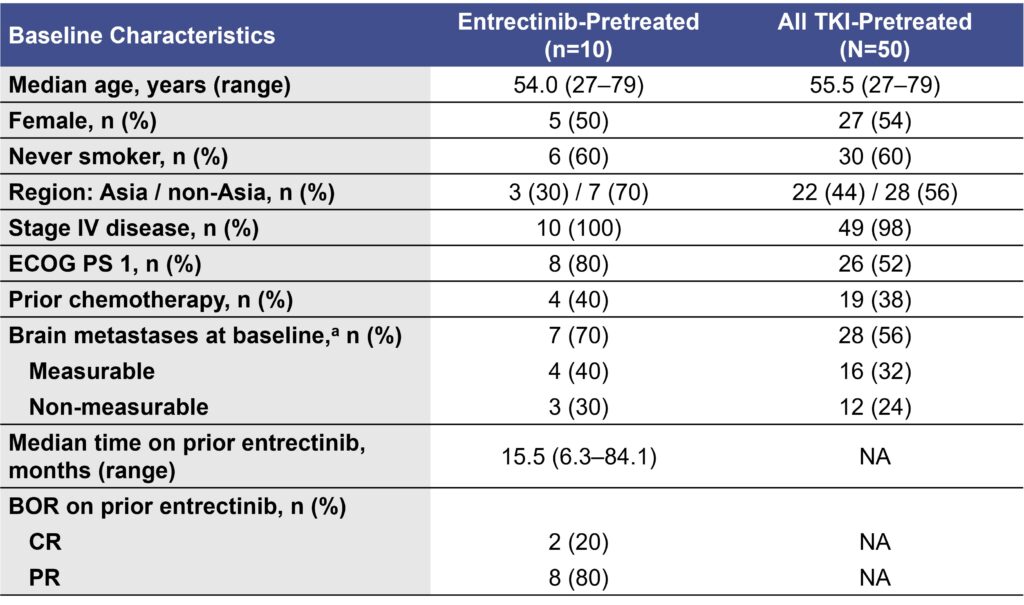
Results: Baseline Characteristics

Patient Demographics and Baseline Characteristics

aAssessed by IRC per mRECIST v1.1.

  • Among entrectinib-pretreated patients, entrectinib was the most recent anticancer therapy prior to taletrectinib, with all patients having experienced disease progression on entrectinib
  • Seven patients had baseline brain metastases (measurable and non-measurable) per mRECIST v1.1 and four patients had received prior chemotherapy

Results: Efficacy

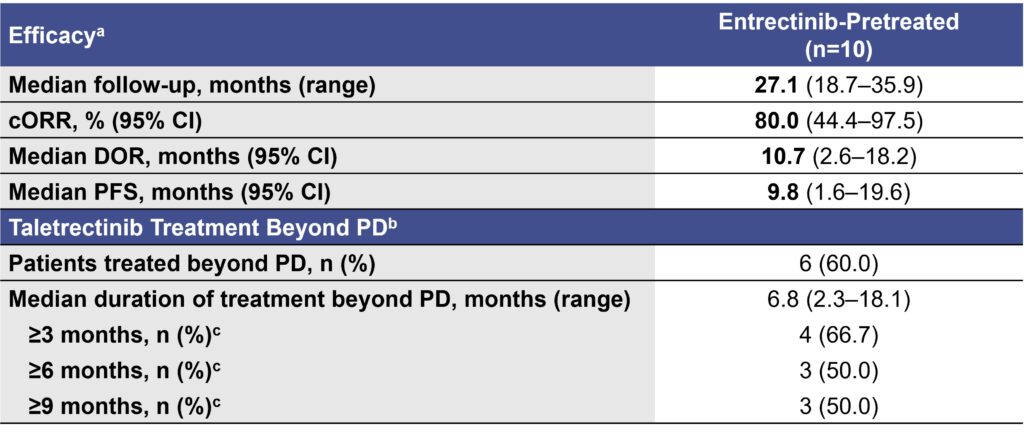
Taletrectinib Demonstrated Robust and Durable Efficacy in Entrectinib-Pretreated Patients
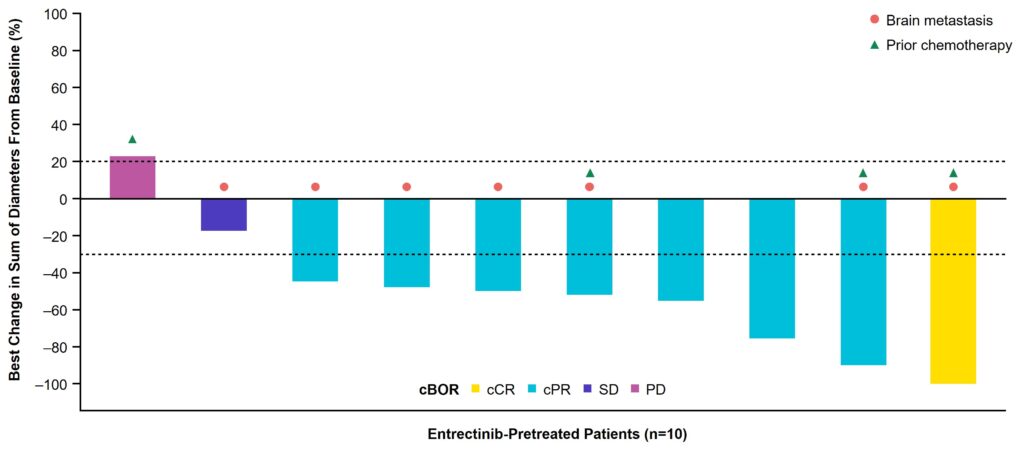
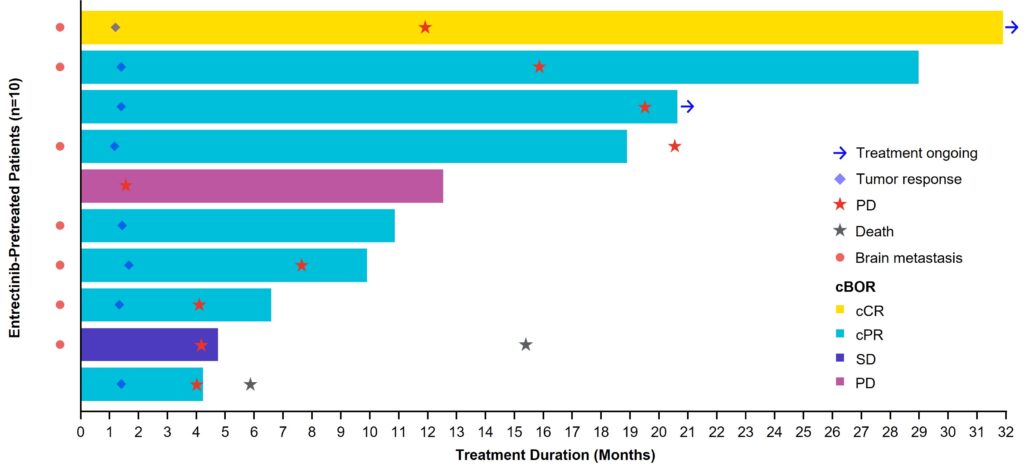
Data cutoff: August 31, 2025. aAssessed by IRC per RECIST v1.1 in patients with ≥1 measurable lesion at baseline who received ≥1 dose of taletrectinib. bPer study protocol, patients were allowed to receive taletrectinib after PD if the investigator considered the patient to still be experiencing clinical benefit, and after discussion with the sponsor. This analysis includes patients who received taletrectinib treatment for ≥1 full cycle after the date of first investigator-assessed PD. cPercentages based on number of patients who continued treatment beyond first investigator-assessed PD.

  • Among the seven entrectinib-pretreated patients with baseline brain metastases (measurable and non-measurable), IC-ORR was 57.1% (95% CI, 18.4–90.1) and median IC-PFS was 13.7 months (95% CI, 4.3–NR)
  • Six entrectinib-pretreated patients continued taletrectinib treatment after investigator-assessed PD for a median of 6.8 months (range, 2.3–18.1)

Results: Safety

  • The median duration of taletrectinib exposure in patients who received prior entrectinib treatment was 11.7 months (range, 4.2–31.9), with half of the patients receiving taletrectinib for at least 12 months
  • AEs of interest commonly associated with entrectinib, such as weight gain, visual disorders, or congestive heart failure, were not observed with taletrectinib in the population reported here
  • Despite a small sample size, the overall safety profile of taletrectinib in entrectinib-pretreated patients was consistent with that observed in the full TKI-pretreated cohort
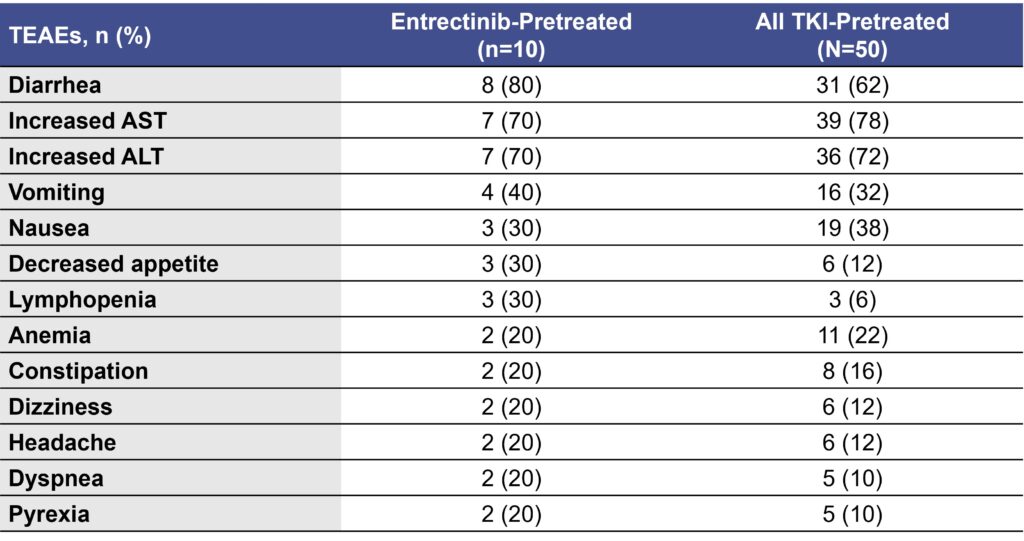
Most Frequent TEAEs Occurring in ≥20% of Entrectinib-Pretreated Patients

Data cutoff: August 31, 2025.

Conclusions

  • With longer follow-up, taletrectinib continued to demonstrate high overall and IC response rates in patients with ROS1+ NSCLC who were previously treated with entrectinib, another CNS-active ROS1 TKI
    • Confirmed ORR was 80% with a median DOR and median PFS of approximately 11 months and 10 months, respectively
    • Among entrectinib-pretreated patients, 60% continued treatment with taletrectinib beyond first PD, with half of those continuing for ≥9 months
    • Among patients with baseline brain metastases, median IC-PFS was approximately 14 months
  • Among patients previously treated with entrectinib, the safety profile of taletrectinib was consistent with that observed in the full TKI-pretreated cohort
  • These data support the use of taletrectinib as a subsequent treatment option for patients with ROS1+ NSCLC after prior entrectinib treatment and suggest sustained clinical benefit and tolerability of taletrectinib treatment beyond radiographic disease progression

Abbreviations

AE, adverse event; ALT, alanine aminotransferase; AST, aspartate aminotransferase; BOR, best overall response; c, confirmed; CI, confidence interval;
CNS, central nervous system; CR, complete response; DOR, duration of response; ECOG PS, Eastern Cooperative Oncology Group performance status; IC, intracranial; IRC, independent review committee; (m)RECIST v1.1, (modified) Response Evaluation Criteria in Solid Tumors version 1.1; NA, not available; NR, not reached; NSCLC, non-small cell lung cancer; ORR, objective response rate; OS, overall survival; PD, progressive disease; PFS, progression-free survival; PR, partial response; QD, once daily; ROS1, ROS proto-oncogene 1; SD, stable disease; TEAE, treatment-emergent adverse event; TKI, tyrosine kinase inhibitor; TTR, time to response.

References

  1. Katayama R, et al. Nat Commun 2019;10:3604
  2. Nagasaka M, et al. Future Oncol 2023;19:123–135
  3. IBTROZI® (taletrectinib). Prescribing Information. Nuvation Bio Inc. 2026
  4. Nippon Kayaku. IBTROZI® Capsules 200mg (taletrectinib) has been approved in Japan. Accessed October 01, 2026; https://www.nipponkayaku.co.jp/english/news/detail.php?n=20250919_6G5AI1Y7
  5. Nuvation Bio. Nuvation Bio Receives Approval from China’s NMPA for Taletrectinib. Accessed October 01, 2026; https://investors.nuvationbio.com/news/news-details/2025/Nuvation-Bio-Receives-Approval-from-Chinas-National-Medical-Products-Administration-for-Taletrectinib-for-Patients-with-Advanced-ROS1-positive-Non-Small-Cell-Lung-Cancer
  6. Bazhenova L, et al. Cancer Res 2026;86(8_Suppl):CT300
  7. Liu G, et al. Cancer Res2026;86(8_Suppl):CT244

Acknowledgments

  • We would like to thank all patients who participated in this study, the study investigators, and their staff
  • This study was sponsored by Nuvation Bio Inc.
  • Medical writing support was provided by Werner Gerber, PhD, of Ashfield MedComms, an Inizio company, and was funded by Nuvation Bio Inc.

Disclosures

The presenting author, Maurice Pérol, declares the following potential conflicts of interest: Advisory boards: AbbVie, Amgen, AstraZeneca, Bristol Myers Squibb, Daiichi Sankyo, Eisai, Eli Lilly, Janssen, MSD, Novartis, Novocure, Pfizer, PharmaMar, Sanofi, and Takeda; Advisory roles: AnHeart Therapeutics, AstraZeneca, Janssen, MSD, Nuvation Bio, and Pfizer; Coordinating PI: Amgen; Expert testimony: AstraZeneca and Bristol Myers Squibb; Invited speaker: Amgen, AstraZeneca, Boehringer Ingelheim, Bristol Myers Squibb, Chugai, Daiichi Sankyo, Eli Lilly, Illumina, Ipsen, Janssen, MSD, Novocure, Pfizer, Roche, Sanofi, and Takeda; Local PI: AbbVie, Amgen, AnHeart Therapeutics, AstraZeneca, Bristol Myers Squibb, Daiichi Sankyo, Eli Lilly, MSD, Nuvation Bio, Roche, Taiho, and Takeda; Principal investigator: Amgen; Research grant: AstraZeneca, Boehringer Ingelheim, Roche, and Takeda; Steering committee member: Amgen, Daiichi Sankyo, and Eli Lilly; Trial chair: Amgen

Explore our other publications